
Oral Radiology Practice Questions
Oral radiology questions test both technique and interpretation. This set covers intraoral techniques, panoramic and cephalometric radiography, cone-beam CT, radiation protection, normal radiographic landmarks, interpretation of caries, restorations, periodontal and periapical findings, differential diagnosis of jaw lesions, and choosing the right imaging modality. The AFK, INBDE, ORE and ADC use radiology in two ways: direct questions on errors, dose and selection criteria, and image-based questions in which you must recognise a landmark or lesion. Knowing why a panoramic image is distorted is as useful as knowing what a lesion looks like.
10 questions · answers and explanations revealed as you go · no sign-up
Questions
Question 1 of 10
Imaging Modality Selection & Correlation
When CBCT is justified for a localized problem, which field of view is generally preferred?
The answer is B.
A task-limited small field generally reduces exposure and improves focused resolution. Modality choice should answer the clinical question with adequate quality and justified exposure. Expected tissue contrast, field of view, artifacts, and whether the result will change management are considered.
Question 2 of 10
Panoramic Radiography
What is a major advantage of panoramic radiography?
The answer is A.
Panoramic radiography provides broad bilateral coverage of teeth, jaws, parts of the maxillary sinuses, and related structures in one image. Its spatial resolution and projection geometry are less suitable for subtle caries or precise measurements. It uses ionizing radiation and retains magnification and distortion.
Question 3 of 10
Cone-Beam CT (CBCT)
What implant-planning question can CBCT answer better than a two-dimensional image?
The answer is C.
Cross-sectional CBCT can demonstrate ridge width, angulation, concavities, and spatial relationships to the mandibular canal, sinus, nasal floor, and neighboring roots when three-dimensional information is needed. Plaque, shade, and tongue movement require clinical or other methods rather than ionizing imaging.
Question 4 of 10
Intraoral Radiographic Techniques
In the paralleling technique, how is the receptor positioned relative to the tooth's long axis?
The answer is C.
The paralleling technique places the receptor parallel to the tooth's long axis and directs the central ray perpendicular to both tooth and receptor. A holder and increased source distance help control geometry. The method generally gives more accurate dimensions than bisecting-angle projections when anatomy permits placement.
Question 5 of 10
Radiographic Interpretation, Caries & Restorations
How does an amalgam restoration generally appear on a dental radiograph?
The answer is D.
Amalgam is highly radiopaque because of its metallic composition and usually has well-defined contours. This helps reveal overhangs, voids, and marginal relationships, although superimposition can limit evaluation. Radiolucent materials and soft-tissue shadows have distinctly different appearances.
Question 6 of 10
Differential Diagnosis of Jaw Lesions
Which phrase describes a uniformly hazy mineralized jaw pattern that obscures normal trabeculae?
The answer is D.
Ground-glass describes fine homogeneous opacity with loss of normal trabecular definition, classically considered in fibro-osseous change. Border, internal structure, location, tooth effects, and clinical findings are integrated. Imaging narrows the differential, while additional views or tissue diagnosis are selected according to risk.
Question 7 of 10
Radiographic Interpretation, Periodontal & Periapical
Which dental condition commonly produces a periapical radiolucency?
The answer is C.
Necrotic pulpal infection can exit through the apical foramen and cause apical periodontitis, granulomatous tissue, or a radicular cyst pattern, all potentially radiolucent. A radiographic lucency alone does not identify histology; pulp testing, symptoms, restorability, and serial findings establish the endodontic relationship.
Question 8 of 10
Cephalometric Radiography
What is the purpose of a cephalostat during cephalometric radiography?
The answer is A.
A cephalostat uses ear rods and other positioning guides to stabilize the head in a reproducible relationship to the x-ray source and receptor. Standardization supports measurement and serial comparison. It does not eliminate all projection magnification, require movement, or place the receptor intraorally.
Question 9 of 10
Normal Anatomic Landmarks (Radiographic)
A U-shaped radiopacity above the maxillary first molar region commonly represents what?
The answer is D.
The zygomatic process often appears as a J- or U-shaped opacity above maxillary molars. Location, continuity of cortical borders, tooth vitality, symmetry, and altered projection geometry help distinguish anatomy from disease. A normal landmark should be correlated with the clinical examination before invasive treatment is considered.
Question 10 of 10
Radiation Protection
Why is a protective apron not a substitute for beam optimization?
The answer is A.
Aprons may reduce selected scatter exposure under particular protocols, but the greatest protection comes from justification, collimation, efficient receptors, optimized settings, positioning, and avoidance of repeats. Shielding cannot rescue an unnecessary examination or poorly controlled primary beam and should not obscure needed anatomy.
Choose an answer to reveal the explanation.
Related anatomy diagrams
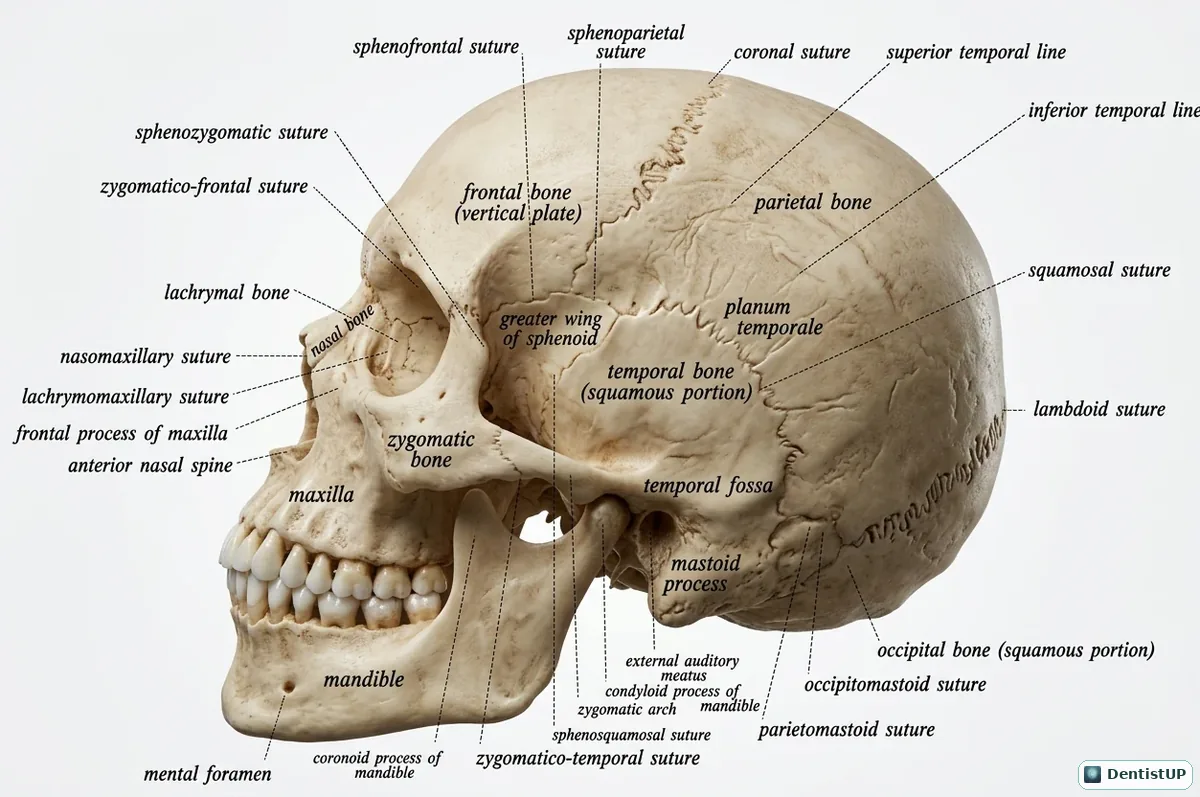
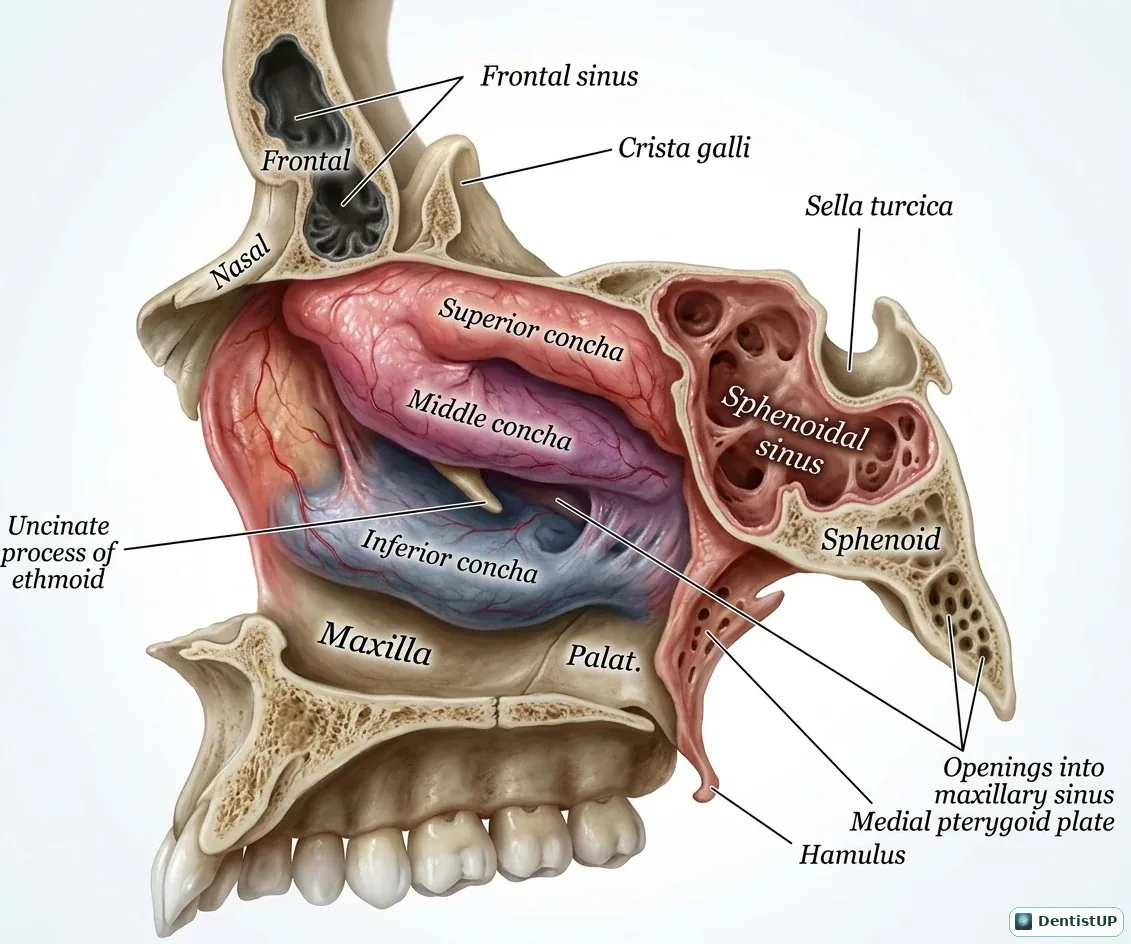
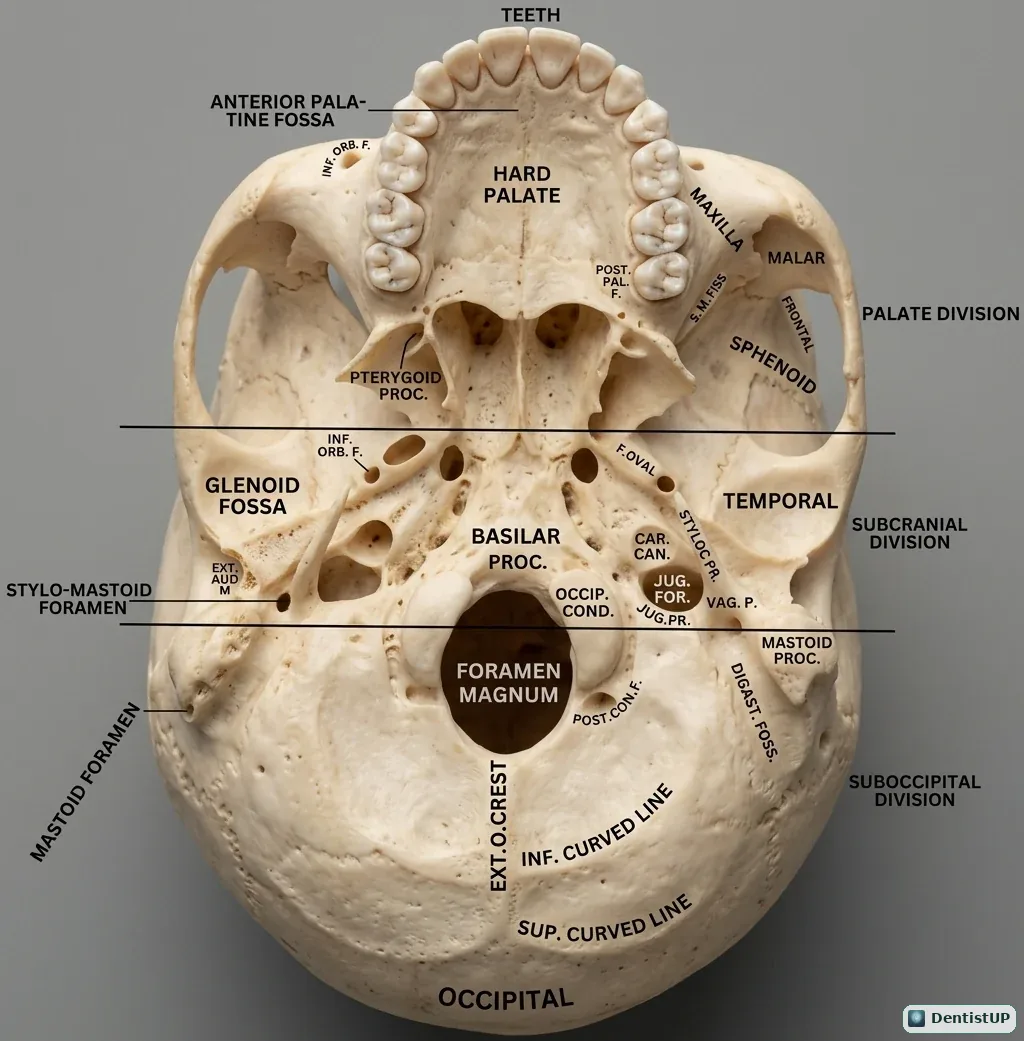
More branches
Full mock exams
DentistUP is an independent educational platform. Socket Science is not affiliated with, endorsed by, sponsored by, or approved by NDEB, INBDE, JCNDE, ADA, GDC, ORE, ADC, or any other examination authority. DentistUP does not contain official or recalled examination questions and does not guarantee examination outcomes. Educational content, not patient-specific clinical advice.